What the Anion Gap Indicates
The anion gap is a simple way to examine the relationship between key electrolytes in the circulation and to help screen for metabolic acidosis. It compares the positive particles, especially sodium, with the primary negatively charged particles, especially chloride and bicarbonate. Because not all charged substances are directly measured on a basic chemistry panel, the anion gap helps approximate the amount of unmeasured anions in the bloodstream.
In clinical practice, the anion gap is a valuable clue during serum chemistry review. It does not diagnose a condition by itself, but it can suggest an acid-base disorder that deserves further evaluation. A high value may signal excess acids in the blood, while a normal value can still reflect a meaningful disturbance in acid-base balance.
Because the calculation uses standard blood chemistry results, it is often one of the initial numbers clinicians use to interpret lab results. It can guide a focused clinical assessment of whether the patient has a true metabolic problem, a simple electrolyte pattern change, or a mixed disorder.
Think of the anion gap as a useful diagnostic tool for identifying hidden contributors to metabolic derangement. When there is a mismatch between the measured cations and anions, the difference may point to retained acids, changes in albumin, or another imbalance affecting overall chemistry.
How to Operate an Anion Gap Calculator
An anion gap calculator is designed to help you quickly calculate anion gap values from common lab findings. The calculator usually asks for serum sodium, serum chloride, and serum bicarbonate. After providing those laboratory values, the calculator applies the formula and displays the result for quick review.
This is especially useful when you want to differentiate causes of a low bicarbonate or suspected acidosis. If the bicarbonate level is reduced, the anion gap can help identify whether acids are increasing or whether bicarbonate is being lost and replaced by chloride.
To use effectively the calculator properly:
- Enter the current serum sodium value from the chemistry panel. Input the serum chloride value. Input the serum bicarbonate value. Assess the result in the context of the patient’s symptoms and other laboratory values.
The calculator is not a substitute for a full diagnosis. Instead, it is a simple way to support a clinical assessment and identify whether the pattern fits a high gap acidosis or a normal gap acidosis. Because acid-base patterns can be mixed, the result should always be interpreted with the rest of the serum chemistry profile and the overall presentation.
Anion Gap Formula and Reference Ranges
The usual anion gap formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
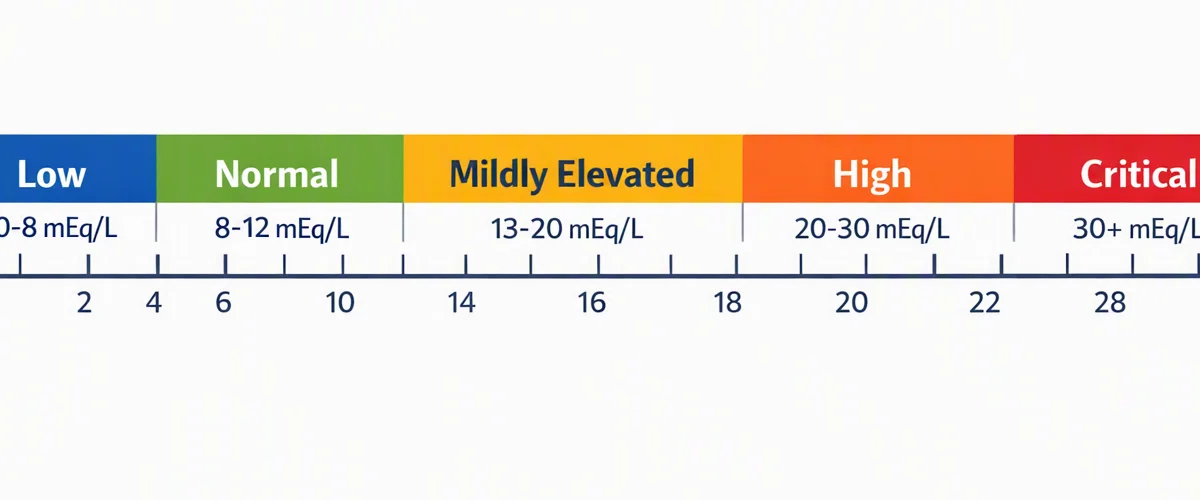
This equation estimates the gap between measured cations and measured negative ions. A higher result suggests more unmeasured anions are present. The specific normal range depends on the testing method and analyzer used, so the reported reference range from the lab should always be checked.
A lot of clinicians think of the normal range as a relatively narrow window, but it is important to use the range provided by the individual lab. A result that seems elevated in one setting may be considered normal in another if the lab method differs.
Albumin matters because it is a key negatively charged protein in blood and plays a major role in the measured gap. Since albumin is not always accounted for directly, low values can make the anion gap appear incorrectly normal or low. That is why the albumin-corrected anion gap can be more useful when albumin is abnormal.
When using the formula as a screening tool, remember that the goal is not only to identify a number outside the normal range. The goal is to interpret the pattern of acid-base balance and whether the numbers suggest a hidden cause of metabolic acidosis.
High Anion Gap Acid-Base Disorder
Increased anion gap metabolic acidosis occurs when acids collect in the body and increase the number of unmeasured anions. This is among of the most important uses of the anion gap because it helps identify reasons of serious illness that may require urgent treatment.
Common causes include lactic acidosis, ketoacidosis, and renal failure. In lactic acidosis, lactate accumulates when tissue oxygen delivery or utilization is impaired. In ketoacidosis, ketone bodies accumulate due to insulin deficiency, starvation, or another major metabolic stress. In renal failure, the kidneys cannot effectively eliminate acid loads, leading to retention of acids in the blood.
Other causes may also produce a high gap pattern, but these three are among the most clinically important. The anion gap reveals a pattern that suggests the acidosis is not simply due to bicarbonate loss. Instead, it points to added acids that alter the chemistry profile.
A patient with metabolic acidosis and a high anion gap may also have tachypnea, nausea, altered mental status, or signs of systemic illness. The calculator can detect the abnormal pattern early, but the next step is to identify the cause through history, exam, and additional tests.
When the gap is elevated, it is helpful to ask whether the clinical picture fits a toxin exposure, shock state, diabetes-related crisis, or kidney dysfunction. This is where the anion gap becomes a practical screening tool rather than just a formula.
Normal Anion Gap Metabolic Acidosis
Non–anion gap metabolic acidosis is also called normal anion gap metabolic acidosis. In this pattern, bicarbonate drops, but chloride increases to preserve the gap within the normal range. That is why it is sometimes called chloride-related acidosis.
Typical causes include diarrhea and renal tubular acidosis. With diarrhea, bicarbonate is depleted from the gastrointestinal tract. With renal tubular acidosis, the kidneys do not properly acidify the urine or process acid-base transport, which leads to persistent acidosis despite having a normal gap.
This pattern is clinically important because a normal value does not rule out a meaningful acid-base problem. A patient can still have metabolic acidosis even when the gap is not elevated. The calculator helps reveal whether the low bicarbonate is being balanced by a rise in chloride, which is characteristic of this type of disorder.
Identifying normal anion gap metabolic acidosis helps distinguish bicarbonate loss from acid accumulation. It also helps direct the workup on fluid loss, renal handling of acid, medication effects, or chronic disorders that affect electrolyte balance.
In short, a normal gap can still point to a serious acid-base disorder. The key is to interpret the result together with the bicarbonate level, the chloride trend, and the patient’s overall clinical picture.

How Albumin Impacts the Anion Gap
Albumin is one of the primary contributors to the result because it carries negative electrical charge in the blood. When albumin is low, the overall count of negatively charged measured anions falls, and the anion gap may seem smaller than expected. That is why hypoalbuminemia can mask a important acidosis.
Albumin correction refines the result to more accurately reflect the actual acid-base status. This is particularly useful when albumin is out of range due to sickness, malnutrition, inflammation, liver disease, or fluid overload. Without correction, a patient with an elevated acid burden may appear to have a near-normal gap.
The reason correction works is tied to protein charge. Albumin contributes a substantial amount of the negative charge in plasma, so changes in its concentration affect the distribution between cations and anions. When albumin falls, the apparent gap drops too, even if the underlying unmeasured anions are elevated.
Using an albumin-corrected anion gap can increase diagnostic accuracy and help prevent missing a high anion gap disorder. In practical terms, if a patient has low albumin and a borderline anion gap, the corrected value may uncover an occult high anion gap metabolic acidosis.
For this reason, it is often advisable to correct for albumin whenever albumin is substantially reduced. This makes the anion gap more trustworthy as a screening marker and improves the interpretation of the serum chemistry panel.
Frequent Causes and Interpretation in Clinical Practice
Evaluating the anion gap requires more than identifying whether it is high or within range. The result should be considered as part of the broader pattern https://jsbin.com/bedecemoyo of acid-base disorders. The best question is not just “Is the gap abnormal?” but “What type of disorder does this pattern suggest?”
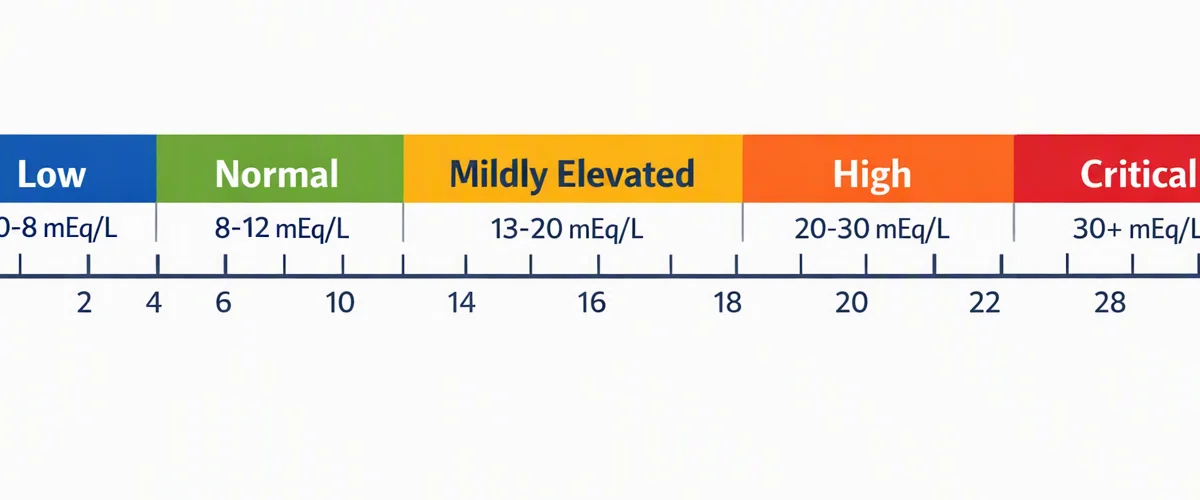
A number of common causes call for special attention. Toxic alcohols can cause a elevated-gap pattern because their metabolites create acid and increase unmeasured anions. Salicylates may also cause complex acid-base changes, sometimes with mixed respiratory and metabolic findings. Uremia, which indicates advanced kidney dysfunction, can lead to acid retention and contribute to a raised gap. These conditions can be serious, so spotting the pattern early matters.
During bedside assessment or in a chart review, the anion gap should be reviewed alongside symptoms, medications, renal function, and exposure history. A rising gap may point to worsening illness, while a low or normal result does not always mean the metabolic problem is gone.
Useful interpretation steps include:
- Examine the serum chemistry pattern for alignment with the reported bicarbonate and chloride values. Evaluate for hypoalbuminemia and apply albumin correction. Assess whether the pattern fits high anion gap metabolic acidosis or normal anion gap metabolic acidosis. Look for clinical clues such as toxin exposure, kidney failure, GI losses, or insulin deficiency. Apply the result to guide follow-up testing and treatment decisions.
This method helps turn a simple number into a important part of the diagnostic process. The calculator becomes a way to spot patterns, refine the differential, and support timely management of an electrolyte imbalance or larger acid-base problem.
FAQ
What is an anion gap calculator used for?
An anion gap calculator is used to calculate anion gap values from routine lab results and help screen for metabolic acidosis. It is a rapid diagnostic tool for detecting an acid-base disorder, especially when the goal is to identify a high-gap pattern or a normal-gap pattern that needs further interpretation.
How do you work out the anion gap from lab values?
Use the the anion gap formula: serum sodium less the sum of the sum of serum chloride and serum bicarbonate. In other words, anion gap = serum sodium - (serum chloride + serum bicarbonate). This formula relies on standard laboratory values from serum chemistry to estimate the amount of unmeasured anions.
What does a high anion gap mean?
A high anion gap often indicates there are extra acids in the blood, which is why it is associated with high anion gap metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, and renal failure. It can also occur with toxic alcohols, salicylates, or uremia.
Why is albumin correction important in the anion gap?
Albumin holds negative charge and strongly influences the gap. With hypoalbuminemia, the measured result may miss the true acid burden. That is why albumin correction or the albumin-corrected anion gap is important for accurate interpretation, especially when trying to correct for albumin in a patient with suspected acidosis.
Can a normal anion gap still indicate metabolic acidosis?
Indeed. A normal value can still occur in normal anion gap metabolic acidosis, also called hyperchloremic acidosis. This pattern is often seen with diarrhea or renal tubular acidosis. So a normal gap does not exclude metabolic acidosis; it just suggests a different cause and pattern of acid-base balance.