Why the Anion Gap Assesses
The anion gap is a computed value from a routine electrolyte panel that supports the assessment of blood test interpretation in suspected acid-base problems. It shows the relationship between major measured ions, especially serum sodium, serum chloride, and serum bicarbonate. In basic terms, the anion gap estimates the amount of unmeasured ions in the blood and can serve as a practical diagnostic marker for certain acid-base problems.
Because the body works to maintain electroneutrality, the total positive and negative charges in blood should be balanced. When measured ions shift, the anion difference can indicate an underlying acid-base disorder. A change in the gap often signals a metabolic derangement such as metabolic acidosis, where acids accumulate or bicarbonate is reduced.
The concept is especially useful in serum chemistry because it gives clinicians a rapid clue about whether the patient may have a high anion gap, a normal anion gap, or a low anion gap. That clue can narrow the list of possible causes and guide further testing.
How an Anion Gap Calculator Works
An anion gap calculator uses a simple calculation formula based on standard laboratory values. Most calculators require serum sodium, serum chloride, and serum bicarbonate. Some calculators also include potassium, which adds a potassium value-based adjustment to the result.
The calculator runs an adjusted calculation that follows the core chemistry of the blood. Sodium is the primary measured cation, while chloride and bicarbonate are major measured anions. The remaining difference helps estimate unmeasured ions. This can be useful in blood test interpretation because the result may show a hidden acid load, a change in bicarbonate level, or an abnormal shift in the sodium chloride balance.
In practice, the calculator is a fast method for understanding whether there is a gap in the measured ions that could indicate a specific problem. It does not replace a full clinical review, but it can be a useful first step in assessing acid-base balance.
Anion Gap Formula With and Without Potassium
There exist two widely used approaches to compute the gap: a traditional formula and a potassium-inclusive formula. This traditional method usually uses sodium, chloride, and bicarbonate. The potassium-inclusive approach adds serum potassium to the cation side of the equation.

A common traditional formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
The potassium-inclusive formula is:
Anion gap = (serum sodium + serum potassium) - (serum chloride + serum bicarbonate)
Both approaches can be valid, but they do not produce the same number. The potassium-added formula usually gives a slightly higher value because potassium is added to the cation total. As a result, the normal range depends on which formula is used and on the laboratory reference range reported by the lab.
Most clinicians focus on whether the result falls within the expected reference interval for that specific method. A calculator should clearly identify whether it is using the traditional or potassium-inclusive approach, since misreading the formula can lead to confusion in clinical interpretation.
How to Input Blood Test Values Properly
Reliable results depend on entering the correct numbers for blood sodium, chloride, bicarbonate, and when applicable blood potassium. These measurements should come from the same specimen and same time period whenever possible, since mixed timing can skew the result.
Below are the key points to check:
- Use the reported serum sodium value precisely as listed. Input serum chloride from the same panel, not a estimated value. Use the measured serum bicarbonate or total CO2 if that is what the lab shows. If the calculator includes blood potassium, enter the serum potassium value from the same blood sample. Review units carefully so the inputs fit the calculator’s expected format.
Small input errors can create a inaccurate low gap result or hide a true high anion gap. If the numbers seem inconsistent with the patient’s condition, recheck the laboratory values before drawing conclusions.
Interpreting a High Anion Gap
A high anion gap usually suggests additional acids are present in the circulation. This is a typical pattern in metabolic acidosis and is frequently called increased gap acidosis. The main causes include lactic acidosis, ketotic acidosis, renal insufficiency, and poisonous alcohols or other poisoning.
In lactate acidosis, lactate rises because of poor oxygen delivery, shock, severe infection, or impaired metabolism. In ketotic acidosis, ketones increase due to insulin deficiency, starvation, or alcohol-related metabolic states. Renal insufficiency can limit acid excretion and let unmeasured acids to build up. Alcohol toxins such as methanol or ethylene glycol can also produce a significant gap because their metabolites are acidic.
When the gap is high, the key question is not only what the number is, but what it means in the larger medical context. Symptoms, medication history, kidney function, glucose, lactate, ketones, and toxicology may all matter. The anion gap is a clue, not the final diagnosis.
Understanding a Normal or Reduced Anion Gap
A within-range anion gap does not exclude acid-base disease. It may simply mean the body’s measured ions are in equilibrium within the usual range. Some forms of metabolic acidosis, especially those with a rise in chloride, may appear as a normal gap rather than a high one.
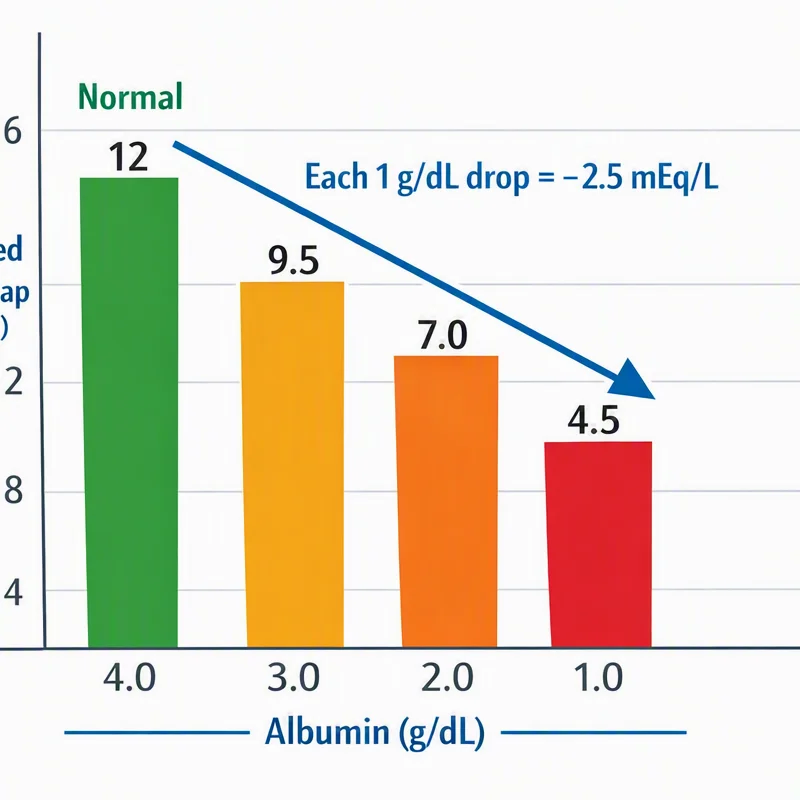
A low anion gap is not as frequent and deserves careful review. One major cause is hypoalbuminemia, because albumin is a negatively charged protein that contributes to the unmeasured anion pool. When albumin is low, the gap can drop even if there is no major acid-base problem.
Other explanations include lab error, hyperchloremia, and paraproteinemia. Hyperchloremia can reduce the gap because chloride rises relative to sodium and bicarbonate. Paraproteinemia, such as that seen in some plasma cell disorders, may also disrupt the expected balance of ions. Because of this, a low value should be checked against the full serum chemistry panel and repeated if needed.
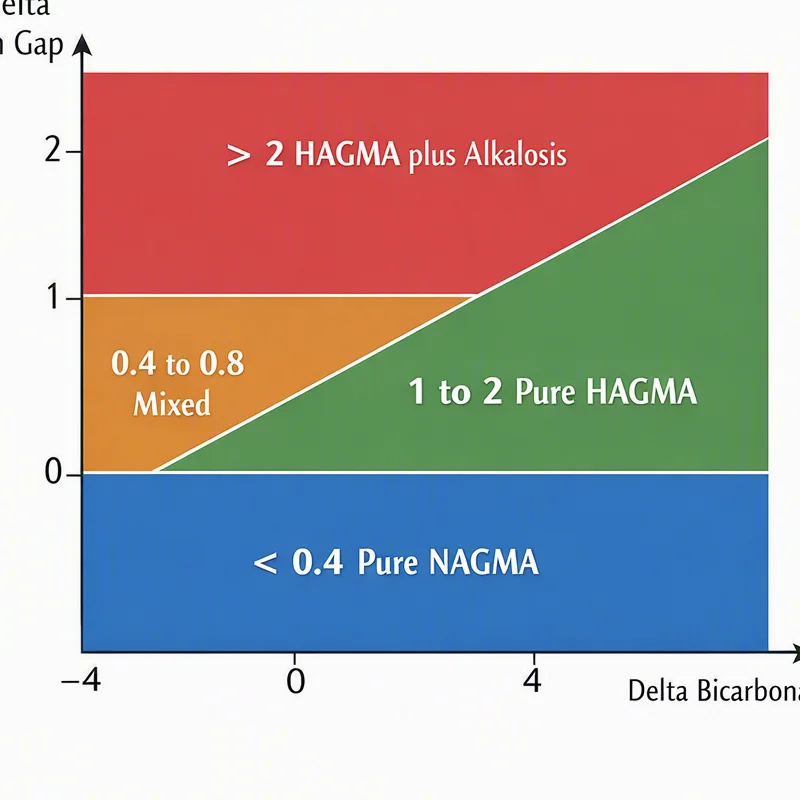
In many cases, the most useful next step is to look for a measurement issue, verify albumin, and evaluate whether the result aligns with the patient’s condition. A low gap can be real, but it can also be a clue that the sample or calculation should be reviewed.
When Potassium Changes the Result
Including serum potassium in the formula can change the final number, but the size of the change is often limited. The reason some calculators provide a potassium-inclusive formula is tied to electroneutrality: potassium is a true cation and contributes to the total positive charge in the blood.
In routine practice, potassium may slightly raise the calculated gap, yet the clinical significance depends on how the result is being used. If the potassium value is normal, the difference between the standard and potassium-inclusive methods may not affect management. If potassium is markedly abnormal, the adjusted anion gap can provide a more complete picture of the electrolyte state.
That said, most clinicians still rely on the traditional approach because it is widely used in labs and textbooks. The potassium-inclusive method can be especially useful when a calculator is designed to capture the full measured cation load and when you want a more detailed view of the patient’s electrolytes.
The practical point is this: potassium matters, but whether it modifies the interpretation depends on the scenario. A calculator that accepts potassium can be a better option for detailed review, while still requiring sound clinical interpretation.
Drawbacks of Internet Anion Gap Calculators
Online calculators are handy, but they have notable limits. To begin with, they use fixed reference limits that may not match every lab’s lab reference range. Different analyzers, patient groups, and formulas can produce different expected values. A number that looks abnormal in one setting may be acceptable in another.
Second, many calculators do not adjust for albumin correction. Because low albumin can lower the anion gap, uncorrected results may underestimate the presence of an acid load. A proper review may require considering albumin as https://anion-gap-formula266.raidersfanteamshop.com/what-drugs-can-cause-high-anion-gap-metabolic-acidosis well as the measured electrolytes.
Also, blood gas and chemistry results are not interchangeable. A venous blood gas may help assess pH and bicarbonate, but its values are not identical to a standard chemistry panel. That difference matters when evaluating metabolic acidosis or a suspected acid-base disorder.
Last, calculators cannot replace clinical context. A result must be interpreted alongside symptoms, medications, kidney function, glucose, ketones, lactate, and other lab findings. The calculator is a aid for pattern recognition, not a standalone diagnosis.
Frequently Asked Questions
What is an anion gap calculator used for?
An anion gap calculator is used for blood test interpretation when reviewing a serum chemistry panel. It helps estimate whether there is a hidden acid load, making it useful for detecting metabolic acidosis, especially high anion gap states. It can also help identify a normal anion gap or low anion gap that may need further review.
Should potassium be included in the anion gap formula?
Potassium is included in some formulas, especially the potassium-inclusive formula, but not all calculators use it. The traditional formula is more common, while the potassium version may better reflect total measured cations in certain cases. Whether to include potassium depends on the calculator design, lab method, and the purpose of the clinical interpretation.
What’s a normal anion gap range?
The expected range depends on the formula and the laboratory. Some labs use a different laboratory reference range for the traditional formula than for the method that includes potassium. Because of this, the preferred approach is to check the result with the specific reference range reported by the laboratory rather than relying on one universal number.
What does a high anion gap mean?
A raised anion gap usually suggests metabolic acidosis from unmeasured acids. Common causes include lactic acidosis, ketotic acidosis, kidney failure, and toxic alcohols or other forms of toxic ingestion. It is a clue that should be interpreted with the rest of the electrolyte panel and the patient’s clinical context.
Can lab error or low albumin cause a low anion gap?
Yes. A low anion gap can stem from lab error or from decreased albumin, since albumin is a major unmeasured anion. Other causes include hyperchloremia and monoclonal protein excess. If the result is unexpected, it is reasonable to confirm the sodium level, potassium level, blood chloride, and blood bicarbonate values and review the full laboratory picture.